A 3D or 4D picture is reconstructed from the same 2D scan — it can make a cleft lip, a spine or the shape of a uterus far easier to read, and at Cosmic it is done inside a scan that already has a medical reason, at no extra charge.
Almost every couple who books a pregnancy scan has seen a 4D video somewhere — a face, a yawn, a hand opening. It is a reasonable thing to want. It is also worth knowing what that picture is made of, because the answer explains both what a 3D or 4D view can genuinely add to your care and why it is never the part of the scan that decides anything.
What 3D and 4D actually are
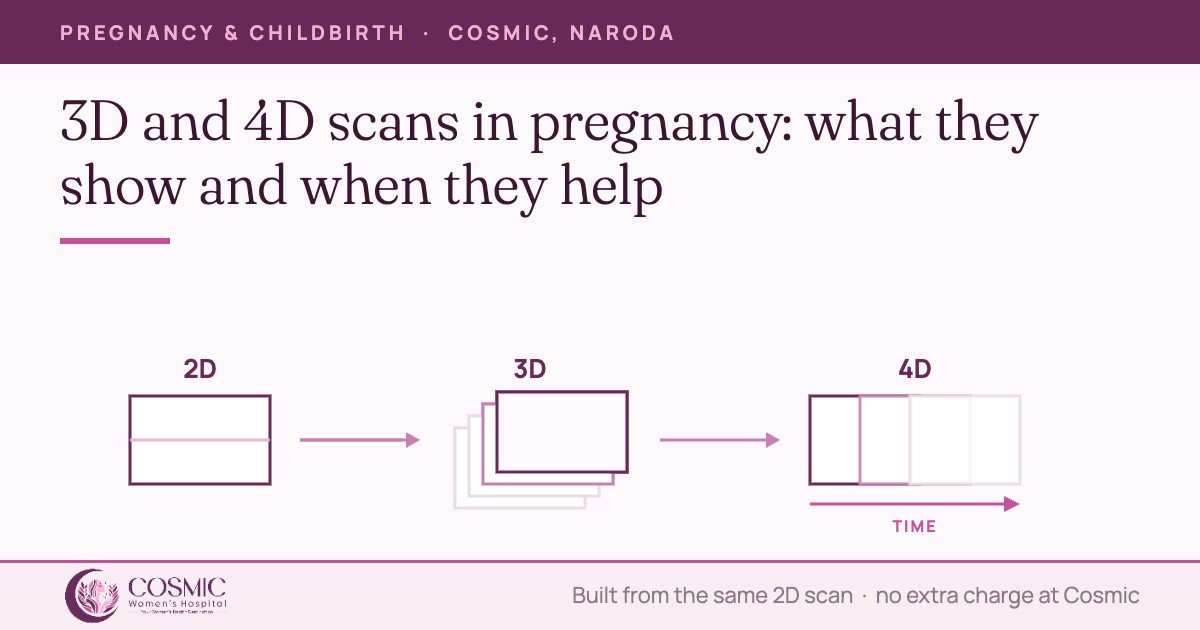
An ordinary obstetric scan is two-dimensional. The probe sends sound into one thin plane at a time and the screen draws that single slice. The person scanning builds the picture of your baby by moving through hundreds of those slices and holding them together mentally.
A 3D scan does the holding-together in software. The machine sweeps through a block of tissue, stores every plane in it as one volume, and then renders a surface from that volume — which is why a 3D image can be rotated and re-sliced after you have gone home. A 4D scan is the same volume refreshed several times a second, so the rendered surface moves. There is no fourth kind of sound wave involved; the fourth dimension is simply time.
The practical consequence matters more than the physics. Because the volume is assembled from 2D planes, the detail in a 3D or 4D picture can never be better than the 2D scan underneath it. Poor position, low fluid, a posterior placenta, scarring or higher body weight degrade a 3D rendering exactly as they degrade a flat image — often more, because the software has less to work with.
Where a 3D view genuinely adds something
Used as a problem-solving tool rather than a photograph, volume imaging earns its place in a few specific situations.
The face and the palate
The surface of the face is exactly the kind of structure a rendered volume shows well. International guidance recognises 3D as a useful tool for examining the fetal face, while stating plainly that it is not part of the routine evaluation (ISUOG, 2022). Where the 2D survey raises a question about the lip, the reconstructed view — and the ability to re-slice the stored volume in planes the probe could not reach at the time — can make a cleft lip easier to define, and the secondary palate behind it is one of the structures volume techniques were developed to reach (AIUM practice parameter, detailed obstetric ultrasound).
The spine and the skeleton
Curvature and segmentation of the spine, and the proportions of the long bones, read more easily on a reconstructed volume than on a single plane. Published practice parameters cite the combination of 2D and 3D in the prenatal assessment of skeletal dysplasias — again as an addition to the standard survey, not a replacement for it.
Outside pregnancy: the shape of the uterus
The strongest evidence for 3D in women’s health is not obstetric at all. A 3D sweep of the uterus can be re-sliced into the coronal plane — the view that shows the outer contour and the cavity together — which is the view a 2D probe cannot produce directly. That is why the ESHRE/ESGE consensus recommends 3D ultrasound as the diagnostic method for congenital anomalies of the female genital tract in women who are symptomatic or in whom an anomaly is suspected, reserving MRI and endoscopy for complex or uncertain cases. In the pooled figures behind that consensus, diagnostic accuracy was 97.6% for 3D ultrasound against 86.6% for 2D.
For a woman being assessed for infertility, or after repeated miscarriage, that is a real difference in a real decision — whether a septum exists, and whether it is the kind that is worth operating on.
Where the 2D scan remains the measurement that counts
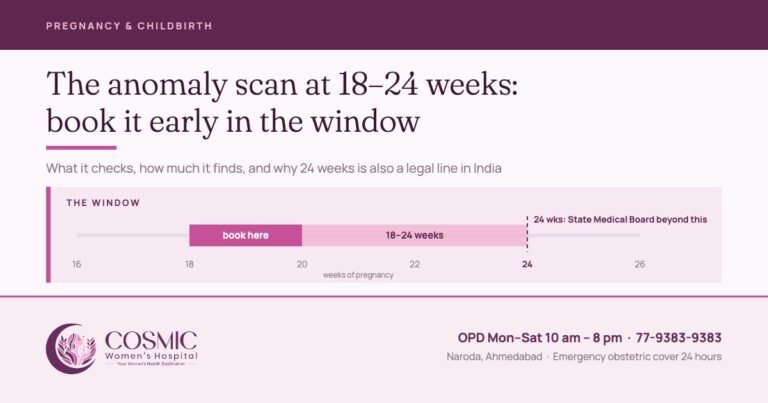
Every decision taken about a pregnancy on the basis of ultrasound rests on 2D measurements and 2D Doppler: the dating length, the nuchal translucency, the four-chamber heart, the head, abdomen and femur, the amniotic fluid, the umbilical artery waveform. The structured anatomical survey at the 18 to 24 week anomaly scan is a 2D survey, organ by organ, and that is what the detection of a structural problem depends on. For the first trimester, 3D and 4D are not used for routine anatomical evaluation at all (ISUOG, 2023).
So a 3D or 4D view is an extra window within a scan, not a different scan. It does not shorten the 2D survey, and a reassuring 4D picture of a face says nothing about the heart.
| Mode | What it produces | What it is used for |
|---|---|---|
| 2D | One live plane at a time | All biometry, the anatomical survey, fluid, placenta, cervix, Doppler — every measurement a decision is based on |
| 3D | A stored volume, rendered as a surface and re-sliceable afterwards | Problem-solving on a question the 2D survey has already raised: the lip and palate, the spine and long bones, and the coronal view of the uterus |
| 4D | The same volume refreshed, so the surface moves | Movement and behaviour — swallowing, hand-to-face, breathing movements; the view families are shown at the end of an indicated scan |
Safety, and why the scan is kept short
Diagnostic ultrasound has been used in pregnancy for decades with no established harm at diagnostic output levels, and 3D imaging uses the same sound energy as 2D — it is the acquisition and display that differ, not the beam. The professional position is nonetheless unambiguous: exposure is kept as low as reasonably achievable, the thermal and mechanical indices are displayed and watched, and the examination lasts as long as the clinical question needs and no longer. For Doppler in the first trimester, guidance sets a thermal index at or below 1.0 and an exposure usually no longer than five to ten minutes (ISUOG, 2023).
That principle is the whole reason volume imaging is treated as part of an indicated examination rather than an entertainment. The American Institute of Ultrasound in Medicine strongly discourages the non-medical use of ultrasound, and the US Food and Drug Administration discourages keepsake videos while accepting that keepsake images are reasonable when they are produced during a medically indicated examination. The AIUM practice parameter is blunter still about commercial scanning: using a diagnostic ultrasound system for keepsake imaging without a physician’s order may breach local law, and promoting equipment for keepsake videos is an unapproved use of a medical device.
Read together, the position is a sensible one for a patient as well as a regulator. There is no reason to refuse a family the picture. There is good reason for that picture to be taken by the doctor who is already scanning you for a clinical purpose, in a hospital, within a scan that is being reported.
What the law requires at every pregnancy scan. Prenatal sex determination is not done here and is prohibited by law under the Pre-conception and Pre-natal Diagnostic Techniques (Prohibition of Sex Selection) Act, 1994. The sex of the fetus is never disclosed to anyone, by words, signs or in any other manner whatsoever, and no request for it will be entertained — including during a 3D or 4D view, where parents sometimes assume more is visible than is reported. A Form F is completed for every prenatal ultrasound with the written reason for the scan recorded, written consent is taken, and records are maintained as the Act requires. The penalties under the Act apply both to the practitioner and to the person seeking sex determination.
At Cosmic Women’s Hospital
3D and 4D imaging is available on our own machine in Naroda, and there is no additional charge for it — it is not sold as a package or an add-on. It is used within a scan that has a medical reason: an obstetric ultrasound is Rs 1,200 and a colour Doppler study Rs 1,500, and a 3D or 4D view is taken during that examination where it helps answer the question, or at the end of it once the survey is complete.
Your scans are performed and reported by Dr. Rahul Khatri and Dr. Bhargavi Khatri themselves — the consultants looking after the pregnancy, not a separate scanning service. If something on the scan needs a more detailed assessment than an obstetric unit should be making on its own, we arrange a targeted repeat scan here and refer you to an expert fetal medicine specialist for the detailed evaluation, fetal echocardiography and counselling, while your pregnancy continues to be looked after here.
If you are being assessed for infertility or after repeated miscarriage, a 3D sweep of the uterus is part of what we can do in the same visit. To book, call 77-9383-9383. OPD Monday to Saturday, 10 am to 8 pm.
Questions worth asking at the scan
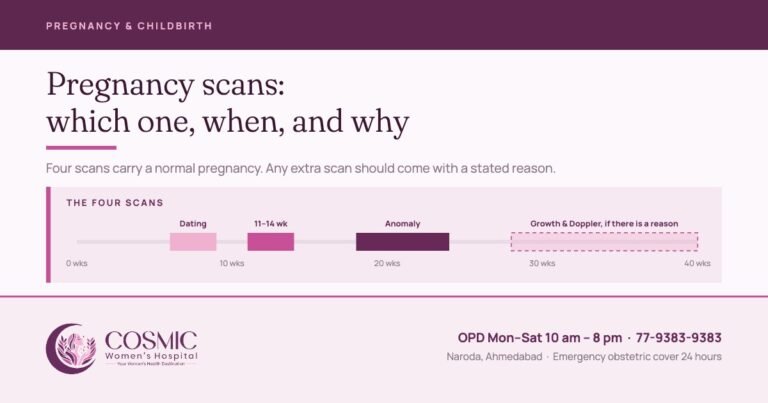
- What is this scan for today? Dating, screening, anatomy, growth and Doppler are different examinations with different windows — the guide to pregnancy scans sets out which is due when.
- Was the 2D survey complete? That, not the 3D picture, is the finding.
- Is there anything that needs a repeat look? Position, fluid or maternal body habitus can leave one structure unseen, and saying so is normal practice rather than bad news.
- Who is reporting it, and when do I get the report? A scan without a signed report is an image, not an examination.
Sources
- ISUOG Practice Guidelines (updated): performance of the routine mid-trimester fetal ultrasound scan. Ultrasound in Obstetrics & Gynecology 2022;59:840–856 — 3D as a useful tool for the fetal face, not part of the routine evaluation; ALARA; scanning not to be performed solely for parental entertainment.
- ISUOG Practice Guidelines (updated): performance of the 11–14 week ultrasound scan. Ultrasound in Obstetrics & Gynecology 2023;61:127–143 — 3D and 4D not used for routine first-trimester anatomical evaluation; Doppler thermal index at or below 1.0, exposure usually 5–10 minutes.
- AIUM Practice Parameter for the Performance of Detailed Second- and Third-Trimester Diagnostic Obstetric Ultrasound Examinations — 3D for facial clefts, the secondary palate and skeletal dysplasia; keepsake imaging without a physician’s order; indication-driven examination.
- AIUM Official Statement: Prudent Use and Safety of Diagnostic Ultrasound in Pregnancy (2020) — strongly discourages the non-medical use of ultrasound.
- US Food and Drug Administration, Ultrasound Imaging (updated September 2024) — keepsake videos discouraged; keepsake images reasonable if produced during a medically indicated examination.
- Grimbizis GF, Di Spiezio Sardo A, Saravelos SH, et al. The Thessaloniki ESHRE/ESGE consensus on diagnosis of female genital anomalies. Gynecological Surgery 2016;13(1):1–16 — 3D ultrasound recommended for diagnosis; pooled accuracy 3D 97.6%, sonohysterography 96.5%, 2D 86.6%.
- Ministry of Health and Family Welfare, Handbook on the PC&PNDT Act, 1994 and Rules with Amendments — registration, Form F, recorded indication, consent, non-disclosure and penalties.
Written by the clinical team at Cosmic Women’s Hospital & IVF Center, Naroda, Ahmedabad.
Medically reviewed by Dr. Bhargavi Khatri
MBBS, MS Obgy (Gold Medalist), FRM
Consulting Obgyn, Infertility & IVF Specialist
Reviewed on 7 October 2026. This article is general information about ultrasound in pregnancy and gynaecology. It is not a substitute for assessment of your own pregnancy, and the findings and advice in your case come from your own scan, examination and reports.
Book a consultation
Tell us how we can help and we will call you back.

Cosmic Women's Hospital
Cosmic Women’s Hospital & IVF Center is a registered Level 2 ART clinic in Naroda, Ahmedabad — obstetrics, gynaecological surgery, IVF and ICSI, with ultrasound in-house and 24-hour emergency obstetric cover. Articles here are written by the clinical team and medically reviewed by Dr. Rahul Khatri or Dr. Bhargavi Khatri before publication.