The 18-to-24-week scan is the one that goes over the baby head to toe — here is what is on the checklist, how much of it is actually found, and why the week you book it in matters more in India than anywhere else.
The anomaly scan is the longest scan of the pregnancy and the one women ask the fewest questions about. It is booked, it is done, and the report comes back saying no gross congenital anomaly detected — a sentence that sounds like a guarantee and is not one. Three things are worth knowing before you go in: what is on the checklist, how much of it ultrasound reliably finds, and why the week you book it in matters in India in a way it does not elsewhere.
The window, and why 23 weeks is too late
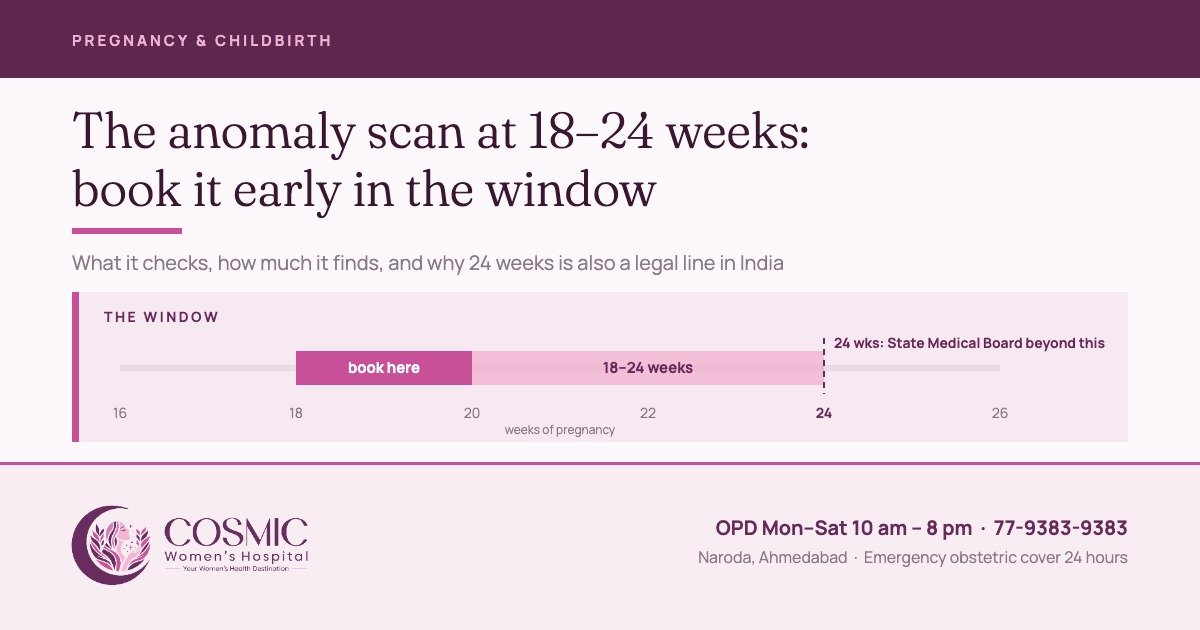
The International Society of Ultrasound in Obstetrics and Gynecology puts the routine mid-trimester scan at 18 to 24 weeks, and allows the timing to be adjusted for technical reasons.1 England’s national programme offers it at 18+0 to 20+6 weeks and requires it to be completed by 23+0.2 NICE schedules exactly two scans in an uncomplicated pregnancy — one at 11–14 weeks, one at 18+0 to 20+6 — and none routinely after that.3 The WHO recommends at least one scan before 24 weeks for every pregnancy.4
Every one of those numbers stops at 24 weeks, and in India that is not only a clinical matter. Under the MTP Rules a pregnancy may be terminated up to 24 weeks on the advice of two registered medical practitioners where there is a substantial risk of fetal abnormality; past 24 weeks the decision needs the approval of a State Medical Board, and only where the abnormality is substantial.6
That is the practical argument for booking early in the window rather than late. A finding at 19 weeks leaves room for a repeat targeted scan, a dedicated fetal heart scan and a genetic result, each of which takes days. The same finding at 23 weeks leaves none, and a decision that should be made calmly gets made against a deadline.
Prenatal sex determination is not done here
Prenatal sex determination is not done at this hospital and is prohibited by law under the Pre-conception and Pre-natal Diagnostic Techniques (Prohibition of Sex Selection) Act, 1994.
The Act places specific duties on any facility using ultrasound in pregnancy: it must be registered before any prenatal diagnostic procedure is carried out; a Form F must be completed and signed for every procedure; the written reasons for doing the scan must be recorded; a notice must be displayed prominently, in English and in the local language, stating that sex determination is not done; and the sex of the fetus must not be disclosed to anyone, by words, signs or in any other manner whatsoever. Records are kept for two years.5
The penalties fall on both sides of the conversation. A practitioner faces up to three years and a fine of Rs 10,000 for a first offence, five years and Rs 50,000 for a later one. The person who seeks or abets sex determination faces up to three years and Rs 50,000, and five years and Rs 1 lakh for a later offence — so please do not ask the sonographer, and do not be offended when the answer is no.5
What is actually looked at
The scan is a structured survey, not a browse. The minimum list is set out in the ISUOG guideline, and every structure on it has to be seen and recorded.1
| Part of the baby | What is being looked for |
|---|---|
| Head and brain | Skull shape and integrity, the midline, the ventricles and choroid plexuses, the back of the brain |
| Face and neck | Upper lip for a cleft, the orbits, the profile, the neck |
| Chest and heart | Lungs, the diaphragm, a four-chamber view of the heart with a regular rhythm, and the two great vessels leaving it |
| Abdomen | Stomach on the correct side, both kidneys, the bladder, the cord insertion and an intact abdominal wall |
| Spine | Followed along its length in two planes, with the skin over it intact |
| Limbs | Four limbs, three segments each, both hands and both feet present |
| Measurements | Head circumference, biparietal diameter, abdominal circumference, femur length — plotted against the dates already fixed at the first-trimester scan |
| Around the baby | Position of the placenta, the amount of amniotic fluid, and whether there is one baby or more |
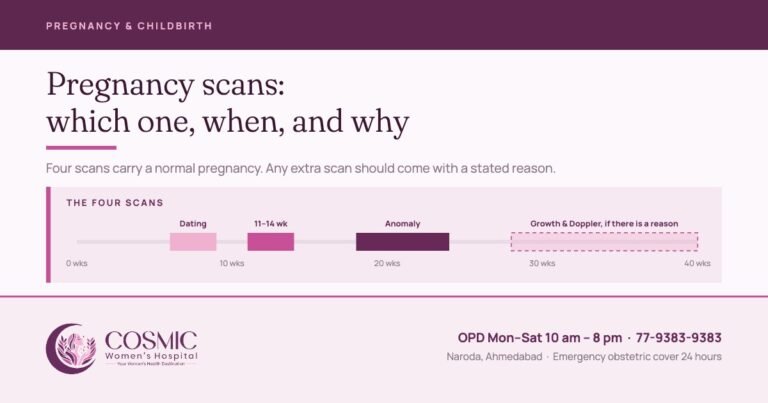
Two things on that last row worry people unnecessarily. If the lower edge of the placenta reaches the cervix at this scan, it does not mean anything is wrong — it means the placenta is looked at again in the third trimester, by which time most have moved up. And routine measurement of the cervix is not recommended where there is no risk factor for preterm birth, so a report that does not mention your cervix has not skipped anything.1 Dates are not revised here either: they were fixed at the 11-to-14-week scan and they stand. How this scan fits with the others is set out in our guide to pregnancy scans.
How much it finds, and how much it does not
This is the part rarely put in writing. England’s national screening programme publishes the detection rate it expects for each of the eleven conditions it looks for at this scan. These are overall published figures for a national programme — they are not this centre’s own detection rates, and no individual unit should be read off them. They are quoted here because they are the clearest honest picture available of what mid-trimester ultrasound can and cannot do.2 The spread is wide.
The shape of the scan follows from that chart. Conditions that change the outline of the body — the skull, the abdominal wall — are found almost every time. Conditions hidden inside a moving four-chamber heart the size of a grape are found about half the time; and heart defects are the commonest serious congenital condition worldwide, ahead of neural tube defects and Down syndrome.10
There is also a category the scan cannot address at all: a genetic or metabolic condition that leaves no structural mark produces a completely normal anomaly scan. Ultrasound looks at structure. It is not a test of the genome.
Soft markers, and why one line in a report is not a diagnosis
Sometimes a scan reports a finding that is not an abnormality but is seen slightly more often in babies with a chromosomal condition — a bright spot in the heart, a slightly full renal pelvis, a choroid plexus cyst. These are called soft markers, and most of them are also seen in perfectly normal babies.
What one is worth depends on what else is known: your age, your first-trimester or cfDNA screening result, and whether any other marker is present. With a low-risk screening result and a single isolated soft marker, nothing comes of it the great majority of the time. Where the scan finds an actual anomaly, or an enlarged nuchal translucency was seen earlier, the position is different — genetic counselling and diagnostic testing should be offered.7
Two sentences are worth carrying into any such conversation. A cfDNA (NIPT) blood test is a screening test — in ACOG’s words, cell-free DNA testing is not equivalent to diagnostic testing — so a reassuring NIPT does not close a question that the scan has opened.7 And an amniocentesis, which does answer it, carries a procedure-related risk of miscarriage of about 0.11%, and chorionic villus sampling about 0.22%, on a meta-analysis of more than 50,000 procedures; the authors’ own conclusion was that these risks are much lower than are currently quoted.8
If something is seen
A finding is the point at which a second, more expert pair of eyes is needed, and that is what happens: where the scan raises a real suspicion, you are referred to an expert fetal medicine specialist for the detailed assessment, the fetal echocardiogram if the heart is in question, and the counselling that goes with it. The referral is made from here and the pregnancy continues to be looked after here.
Most findings are not catastrophic and most do not end a pregnancy. A good many change the plan rather than the outcome — a baby with a correctable problem is better delivered on a planned date, somewhere the right paediatric help is arranged, with everyone expecting it. That is a conversation about where and how you deliver, and it is far easier to have at 20 weeks than at 36.
What “no gross fetal anomaly seen” means on your report
Most anomaly scan reports close with a single line: “no gross fetal anomaly seen”, or one of its variants — “no gross congenital anomaly detected”, “no obvious structural anomaly seen”. It is the most reassuring sentence this scan can produce, and it means something precise.
On this scan, at this gestation, with the views that could be obtained on this day, nothing major was seen in the structures that were examined. “Gross” is a medical word for major — a structural problem large enough to show on ultrasound — not “obvious to anyone”. The guidelines themselves acknowledge that some anomalies are missed even with good equipment in experienced hands, and that some develop only later in pregnancy.1 A normal report substantially lowers the chance of a major structural problem. It does not remove it, and it says nothing about how the baby will grow.
| The line on the report | What it means | What happens next |
|---|---|---|
| No gross fetal anomaly seen / no gross congenital anomaly detected | Every structure on the checklist was seen and looked normal on the day. | Nothing extra. Your routine care continues, including the growth scan at 32 to 34 weeks. |
| Limited views / suboptimal visualisation, often “due to fetal position” | One or more structures could not be seen clearly enough to be called normal. This is not a finding; it is usually down to how the baby was lying. | A short repeat look to complete the views, booked so that it still falls inside the window. |
| A soft marker noted, such as a bright spot in the heart or mild widening of the kidney pelvis | A variation that is common in healthy babies and carries weight only alongside your other results. | Read against your first-trimester screening, as explained under soft markers above. |
| Follow-up advised / review with your obstetrician | Something needs another look or a decision. | Discussed at the same visit, with referral to an expert fetal medicine specialist where there is a real suspicion. |
Three kinds of problem sit outside that line altogether. Conditions that are not structural: many babies with a chromosomal condition such as Down syndrome look structurally normal on this scan, which is why chromosomal risk is assessed by the screening tests, not by the anomaly scan. Conditions too small to see: a small hole between the heart’s pumping chambers is the classic example. And conditions that appear later: some brain, kidney, bowel and bone conditions only become visible in the third trimester. That is why the report line is a statement about this scan, not about the rest of the pregnancy.
When your report reads “no gross fetal anomaly seen”, the consultant who did the scan goes through it with you at the same visit — what was checked, and anything that could not be seen.
Growth is a third-trimester question, answered selectively rather than routinely. Measuring every low-risk baby again in the third trimester has not been shown to reduce the number born small or to improve outcomes; but where a pregnancy is already high-risk or the baby is already known to be small, umbilical artery Doppler does reduce perinatal death and illness — sixteen trials, more than ten thousand babies.9 That is the logic behind watching some pregnancies closely and leaving others alone. How those later scans work is set out in our growth scan and Doppler guide.
At Cosmic, one growth scan with colour Doppler is done routinely at 32 to 34 weeks. Any further growth scans and Dopplers after that are decided on the findings and the history.
At Cosmic
Obstetric ultrasound is done in-house at our Naroda centre, so the scan and the consultation happen in the same visit rather than on two different days. The obstetric scans here are performed and reported by the consultants themselves — Dr. Rahul Khatri and Dr. Bhargavi Khatri — so the person holding the probe is the person who can answer your question while you are still on the couch. Where a scan raises a real suspicion, referral to an expert fetal medicine specialist is arranged from here.
Obstetric ultrasound is Rs 1,200 and colour Doppler Rs 1,500; a new general consultation is Rs 500 and a follow-up Rs 300. OPD runs Monday to Saturday, 10 am to 8 pm, with 24-hour emergency obstetric cover.
One request, and it is the most useful thing in this article: book the anomaly scan for 18 to 20 weeks at the moment your 11-to-14-week scan is reported — not in the twentieth week, when the slot you want may already be taken. Call 77-9383-9383.
Five things worth asking at the scan
- Was every structure on the checklist seen? If a view was incomplete — position, fluid, body habitus — say so on the report and tell me when to come back for it.
- Where is the placenta, and does it need looking at again later?
- Is the amniotic fluid normal?
- If a soft marker is mentioned: what does it change, given my screening result? And what, if anything, would you do about it?
- Do I need any further scan — and by which week? Ask for the week, not “later”.
Sources
- ISUOG Practice Guidelines (updated): performance of the routine mid-trimester fetal ultrasound scan. Ultrasound Obstet Gynecol 2022;59:840–856.
- NHS Fetal Anomaly Screening Programme handbook — 20-week screening scan, and programme test-performance standard FASP-S04. GOV.UK.
- NICE NG201, Antenatal care (2021) — Schedule of antenatal appointments.
- WHO recommendations on antenatal care for a positive pregnancy experience (2016), recommendation B.2.4.
- The Pre-conception and Pre-natal Diagnostic Techniques (Prohibition of Sex Selection) Act, 1994, and Rules — Ministry of Health and Family Welfare handbook.
- The Medical Termination of Pregnancy (Amendment) Act, 2021, and MTP Rules 2021, Rules 3A and 3B.
- ACOG Practice Bulletin No. 226, Screening for Fetal Chromosomal Abnormalities. Obstet Gynecol 2020;136:e48–e69.
- Akolekar R, Beta J, Picciarelli G, Ogilvie C, D’Antonio F. Procedure-related risk of miscarriage following amniocentesis and chorionic villus sampling. Ultrasound Obstet Gynecol 2015;45:16–26.
- RCOG Green-top Guideline No. 31, The Investigation and Management of the Small-for-Gestational-Age Fetus (2013, reviewed 2014).
- WHO fact sheet, Congenital disorders.
Written by the clinical team at Cosmic Women’s Hospital and IVF Center, Naroda, Ahmedabad — a registered Level 2 ART clinic offering obstetrics, gynaecological surgery, IVF and ICSI, with ultrasound in-house and 24-hour emergency obstetric cover.
Medically reviewed by Dr. Bhargavi Khatri — MBBS, MS Obgy (Gold Medalist), FRM. Consulting Obgyn, Infertility and IVF Specialist. Reviewed 30 September 2026.
This article is general information about a screening test and is not a substitute for a consultation. Prenatal sex determination is not done at this hospital and is prohibited by law under the PC&PNDT Act, 1994.
Book a consultation
Tell us how we can help and we will call you back.

Cosmic Women's Hospital
Cosmic Women’s Hospital & IVF Center is a registered Level 2 ART clinic in Naroda, Ahmedabad — obstetrics, gynaecological surgery, IVF and ICSI, with ultrasound in-house and 24-hour emergency obstetric cover. Articles here are written by the clinical team and medically reviewed by Dr. Rahul Khatri or Dr. Bhargavi Khatri before publication.