What actually decides how a baby is born — the small number of situations where there is no real choice, the much larger grey zone where labour is worth attempting, and the questions worth asking before you agree to either.
Almost every woman asks it at the first pregnancy visit, usually near the end and usually a little apologetically: will I need a caesarean? It deserves a better answer than “we will see at the time”.
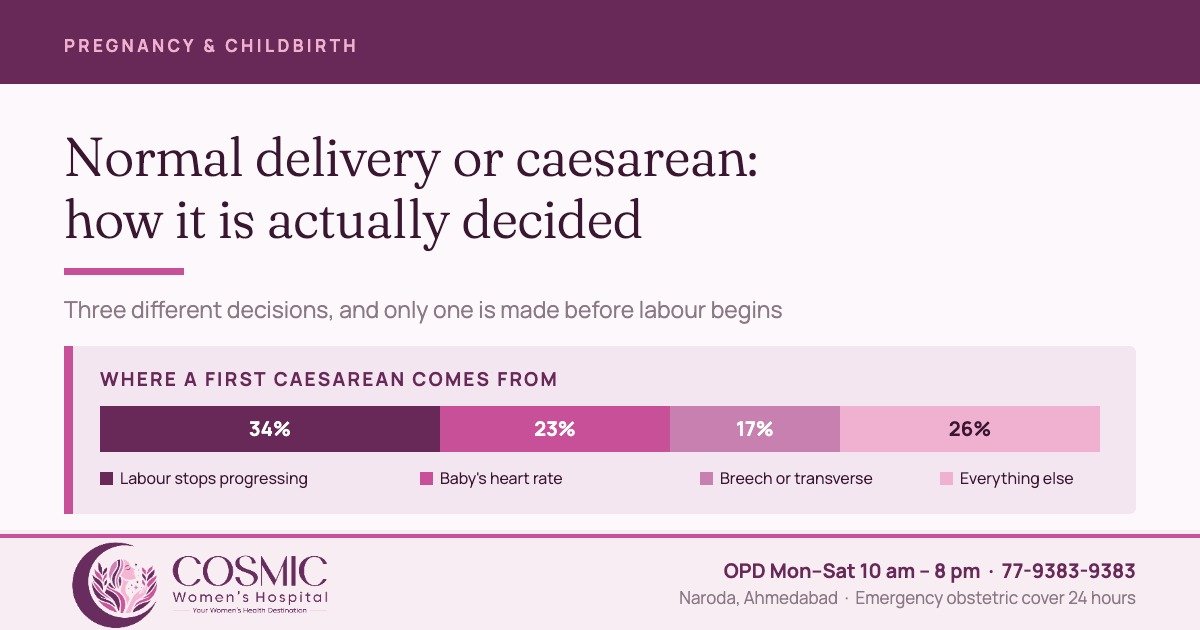
The route of delivery is decided in three different ways at three different moments, and only one of those moments comes before labour begins. Knowing which of the three you are in tells you far more than any statistic about caesarean rates.
Why the question feels loaded in India
The National Family Health Survey (NFHS-5, 2019–21) found that 21.5% of all births in India were by caesarean section, up from 17.2% five years earlier. The split by sector is the number that unsettles people: 47.4% of births in private facilities were caesarean, against 14.3% in government facilities.
That gap is real and it is worth knowing about. But two things are usually said about it that are not quite right. The first is that the World Health Organization recommends a caesarean rate of 10–15%. It no longer does — WHO states plainly that it “does not recommend a specific rate for countries to achieve at population level”. What the evidence supports is narrower: as a country’s rate rises to about 10%, maternal and newborn deaths fall; above 10%, no further reduction in mortality is seen.
The second is that a hospital’s caesarean rate tells you what will happen to you. It does not. A unit that takes referrals of twins, breech babies, previous caesareans and pre-eclampsia will have a higher rate than one that does not, and that is as it should be. WHO’s own advice is to sort caesareans into the Robson groups — parity, onset of labour, gestation, presentation, number of babies — so that rates are compared between like and like rather than read as a scoreboard.
Three different decisions, not one
| When it is decided | What it looks like | How often it applies |
|---|---|---|
| Before labour, caesarean planned | A reason is already present at, say, 36–38 weeks that makes labour unsafe or impossible | The minority of pregnancies |
| Before labour, vaginal birth planned | No such reason; labour is awaited or induced, with the route still open | Most pregnancies |
| During labour | Labour has started and something changes — progress, the baby’s heart rate, the position | Where most first caesareans come from |
When a caesarean is not really a choice
A small group of findings settle the question on their own, and in these situations a planned caesarean is not a preference but the safer route:
| Finding | Why labour is not the route |
|---|---|
| Placenta praevia covering the cervix | The placenta lies over the exit; labour means bleeding |
| Transverse or oblique lie that persists at term | The baby lies across the uterus and cannot descend |
| A previous classical (upper-segment) uterine scar | Rupture risk in labour is unacceptably high |
| Cord prolapse, or abruption with a baby in distress | Emergencies measured in minutes, not hours |
| Obstructed labour, or a baby whose heart rate will not recover | Waiting longer adds risk without adding benefit |
Most of what people treat as fixed indications are not on that list. Twins, a breech first baby, one previous caesarean, a big baby, the mother’s age — each opens a conversation rather than closing it.
The grey zone, where the real conversation happens
A breech baby
Three to four in every hundred babies are still breech at term. Presentation should be checked and recorded from 36 weeks, so that external cephalic version — turning the baby by hand on the abdomen — can be offered from 37 weeks. Across pooled studies the attempt succeeds about 58% of the time, with complications of any kind in 6.1% and serious events under 1%. Where it does not work a planned caesarean is usually the route, and that is a reasonable place to arrive at — but it should be arrived at, not assumed at the first scan that shows a breech.
One previous caesarean
A trial of labour is offered where the previous caesarean was a lower-segment one — a low-transverse scar, no classical or upper-segment scar, and nothing else present that rules labour out. Between 60% and 80% of women who attempt it give birth vaginally; the risk of scar rupture is in the range of 0.5–0.9%, which is small but not nothing, and is the reason a trial of labour belongs in a unit with theatre and anaesthetic cover available at all hours. It is offered at Cosmic and discussed in more detail on our maternity care page.
“Labour is not progressing”
This is the single commonest reason a first caesarean is done, and it is also where the definitions have changed most in the last decade. Slow is not the same as stopped.
Three things follow at the bedside. Admission in the latent phase does not start a countdown. Arrest needs the cervix at 6 cm or more, the membranes ruptured and a defined stretch of genuinely adequate contractions with no change — not one slow hour. And pushing time is measured in hours, with more allowed while mother and baby are both doing well.
What each route asks of the body
Both routes are safe, and neither is free. A vaginal birth carries the risk of a perineal tear at the time and, for some women, of pelvic floor problems in the years afterwards. A caesarean is major abdominal surgery: a wound, a day or two longer in hospital, and a scar on the uterus.
The scar is the part worth thinking about now rather than later. Every caesarean makes the pregnancy after it a little more complicated — the question of trial of labour has to be settled again, and there is a small added risk that the placenta implants into the old scar. If you intend to have more children, that belongs in the conversation today and not at the next delivery.
Questions worth asking
- Is there a reason right now that rules out labour, or are we still waiting to see?
- If a caesarean is being advised, what is the indication, in one sentence?
- If progress is the concern — what is the dilatation, and for how long has it not changed?
- If the baby is breech, has version been offered, and if not, why not?
- After one caesarean, am I a candidate for a trial of labour?
- Whichever route we plan, what happens if it has to change during labour?
At Cosmic. Both consultants manage the full range of obstetrics here — antenatal care, high-risk pregnancy, normal delivery and caesarean section. Antenatal visits run three-weekly through the first trimester, four-weekly in the second, then three-weekly in the seventh month, two-weekly in the eighth and weekly in the ninth, which is what makes presentation and growth known well before term rather than discovered in labour. Ultrasound and colour Doppler are done in-house, theatre and anaesthetic cover are available around the clock, trial of labour is offered after a previous lower-segment caesarean, and a female attendant stays with the patient at all times. OPD Monday to Saturday, 10 am to 8 pm; emergency obstetric cover 24 hours. Call 77-9383-9383.
Further reading on this site: high-risk pregnancy care, maternity care in Naroda, what a first visit involves, and the Naroda gynaecology service.
Legal notice. Prenatal sex determination is not done at Cosmic Women’s Hospital and is prohibited by law under the Pre-Conception and Pre-Natal Diagnostic Techniques (Prohibition of Sex Selection) Act, 1994. Ultrasound here is performed only for medical indications.
General information about how obstetric decisions are made. It is not a substitute for assessment of your own pregnancy.
Sources
- International Institute for Population Sciences. National Family Health Survey (NFHS-5), India, 2019–21 — caesarean delivery by facility type.
- World Health Organization. WHO Statement on Caesarean Section Rates (WHO/RHR/15.02) and accompanying questions and answers.
- American College of Obstetricians and Gynecologists and Society for Maternal–Fetal Medicine. Obstetric Care Consensus No. 1, Safe Prevention of the Primary Cesarean Delivery, 2014 (reaffirmed 2019).
- American College of Obstetricians and Gynecologists. Practice Bulletin No. 221, External Cephalic Version, May 2020.
- American College of Obstetricians and Gynecologists. Practice Bulletin No. 205, Vaginal Birth After Cesarean Delivery, 2019.
Written by the clinical team at Cosmic Women’s Hospital & IVF Center, Naroda, Ahmedabad.
Medically reviewed by Dr. Rahul Khatri — MBBS, MS & DNB Obgy, FMAS, Consulting Obgyn, Laparoscopic & Robotic Surgeon, Director.
Reviewed 25 September 2026.
Book a consultation
Tell us how we can help and we will call you back.

Cosmic Women's Hospital
Cosmic Women’s Hospital & IVF Center is a registered Level 2 ART clinic in Naroda, Ahmedabad — obstetrics, gynaecological surgery, IVF and ICSI, with ultrasound in-house and 24-hour emergency obstetric cover. Articles here are written by the clinical team and medically reviewed by Dr. Rahul Khatri or Dr. Bhargavi Khatri before publication.